
Every 40 seconds, someone in the world has a stroke. Every four minutes, someone dies from one.
Yet despite these numbers, stroke remains one of the most undertreated emergencies in India — not because treatment doesn't exist, but because most people don't act fast enough.
The good news? Stroke care in 2026 looks nothing like it did a decade ago. New guidelines, smarter technology, and a sharper understanding of the brain have fundamentally changed what's possible — if you get to the right place in time.
First, Understand What You're Dealing With
A stroke happens when blood flow to part of the brain is cut off. Without oxygen, brain cells begin dying — rapidly, and often permanently.
There are two types:
- Ischemic stroke — the most common, caused by a blood clot blocking an artery
- Hemorrhagic stroke — caused by a blood vessel rupturing and bleeding into the brain
Both are emergencies. Both demand immediate action.
The FAST rule remains your first line of defence:
F — Face drooping A — Arm weakness S — Speech difficulty T — Time to act. Right now.
What the 2026 Guidelines Have Changed
1. Speed Is No Longer a Suggestion — It's the Treatment
Emergency protocols now demand ultra-fast response from the moment a patient arrives. Pre-hospital identification, immediate triage to stroke-ready centres, and aggressive reduction in "door-to-needle" time are all built into the system.
Why? Because every minute of delay destroys approximately 1.9 million brain cells. This isn't a metaphor. It's biology.
2. Clot-Busting Therapy: Faster, Broader, Smarter
Thrombolysis — medication that dissolves the clot — remains the first line of treatment for ischemic stroke. What's changed is who gets it and how quickly.
The treatment window now extends to 4.5 hours from symptom onset. More importantly, even patients with mild but disabling strokes are now considered for treatment — something previously ruled out. The focus has shifted from excessive testing to decisive action.
3. Mechanical Thrombectomy: A Lifeline Extended
If thrombolysis was a revolution, mechanical thrombectomy was the one after that.
This minimally invasive procedure physically removes the clot from a blocked brain artery using a catheter. And the window to perform it has expanded significantly:
- Standard window: Up to 6 hours from onset
- Extended window: Up to 24 hours in selected cases
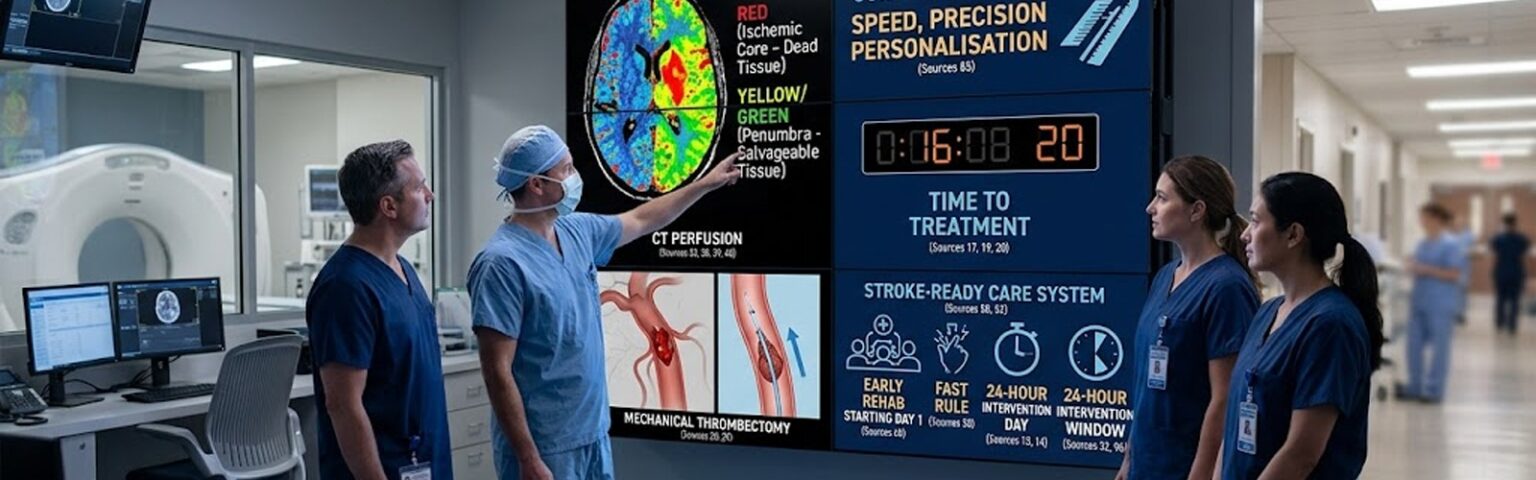
What determines eligibility? Advanced imaging that identifies salvageable brain tissue — the difference between dead tissue and tissue that can still be saved.
Late presentation no longer automatically means no treatment. It means better evaluation.
4. Imaging Has Become the Game-Changer
Modern stroke care runs on precision, and precision runs on imaging.
CT perfusion, MRI diffusion, and angiography now allow us to see exactly:
- What brain tissue has already died (the core infarct)
- What tissue is at risk but still salvageable (the penumbra)
This distinction is everything. It separates patients who will benefit from intervention from those who won't — and it has made stroke treatment genuinely personalised for the first time.
5. Blood Pressure: Controlled, Not Crashed
One of the more counterintuitive updates in stroke care involves blood pressure management. The instinct to aggressively lower BP in a stroke patient turns out to be wrong.
Current guidelines are clear:
- Treat only if BP is dangerously high (above 220/120 mmHg)
- Keep it below 185/110 before administering thrombolysis
- Avoid sudden drops at all costs
The reason: a brain under stress needs adequate blood pressure to maintain perfusion to surviving tissue. Crashing the BP can cause the penumbra — that salvageable zone — to die too.
6. Stroke Care Is Now a System, Not Just a Doctor
This might be the most structural change in the 2026 guidelines. Stroke outcomes are no longer determined solely by physician skill — they're determined by how the entire system around the patient performs.
That system includes:
- Stroke-ready hospitals with rapid imaging capability
- Multidisciplinary teams working in parallel, not sequence
- Integrated ICU and rehabilitation from day one
A brilliant surgeon in a slow system still gets worse outcomes than a well-coordinated team in an efficient one. Systems save lives.
7. Rehabilitation Starts on Day One
Recovery from stroke doesn't begin after discharge. It begins within 24–48 hours of the event.
Early mobilisation, speech therapy, physiotherapy, nutritional support, and swallowing assessments are all now integrated into acute care — not added as afterthoughts. The evidence is unambiguous: patients who begin rehabilitation early regain significantly more function than those who don't.
8. Preventing the Second Stroke
A person who has had one stroke is at substantially higher risk of having another. Secondary prevention is therefore not optional — it is part of the treatment plan.
This means:
- Long-term blood pressure control
- Cholesterol management
- Antiplatelet or anticoagulant therapy depending on stroke type
- Genuine lifestyle change — diet, exercise, smoking cessation
Stroke is often preventable. The second one especially so.
9. Yes, Young People Get Strokes Too
This deserves its own mention because it's still widely underestimated.
Stress, sedentary lifestyles, uncontrolled hypertension, undiagnosed cardiac conditions, and substance use are driving stroke incidence in people in their 30s and 40s. Younger patients often delay seeking care because they don't believe it could happen to them.
It can. And in younger patients, the stakes are even higher — more years of life, more function to preserve.
10. The Future Is Already Here
The next wave of stroke care is already in motion:
- AI-powered imaging that identifies salvageable tissue faster than human reading
- Wake-up stroke detection for patients who don't know when symptoms began
- Advanced endovascular techniques with better navigation and less invasiveness
- Data-driven protocols that match treatment to patient profile in real time
These aren't distant possibilities. They are active areas of practice at leading neurovascular centres today.
The Bottom Line
Stroke management in 2026 is defined by three things: speed, precision, and personalisation.
The technology exists. The protocols exist. The surgical capability exists.
What determines outcomes now is whether the patient — and the people around them — recognise what's happening and act without hesitation.
If you see FAST symptoms — in yourself or anyone around you — call for emergency help immediately. Do not wait to see if it passes. Do not drive yourself. Call. Act. Now.
For expert evaluation and advanced stroke and neurovascular care, consult Dr. Rajesh Reddy Sannareddy, Senior Consultant in Brain, Spine & Endovascular Neurosurgery. Early intervention changes outcomes.
Frequently Asked Questions
Immediate recognition and emergency medical attention. Every minute of delay is brain tissue lost.
Thrombolysis can be given within 4.5 hours. Mechanical thrombectomy can be performed up to 24 hours in selected cases based on imaging.
Yes. Advanced imaging can identify salvageable brain tissue even hours after onset, allowing intervention in selected patients.
Face drooping, arm weakness, speech difficulty — use the FAST rule. Time is critical.
Many strokes are preventable through blood pressure control, cholesterol management, exercise, and lifestyle changes.
A minimally invasive procedure that physically removes a blood clot from a blocked brain artery using a catheter.
Early rehabilitation harnesses the brain's neuroplasticity to maximise recovery of speech, movement, and cognitive function.
Yes. Stroke incidence is rising in adults under 50 due to stress, sedentary lifestyles, uncontrolled hypertension, and substance use.